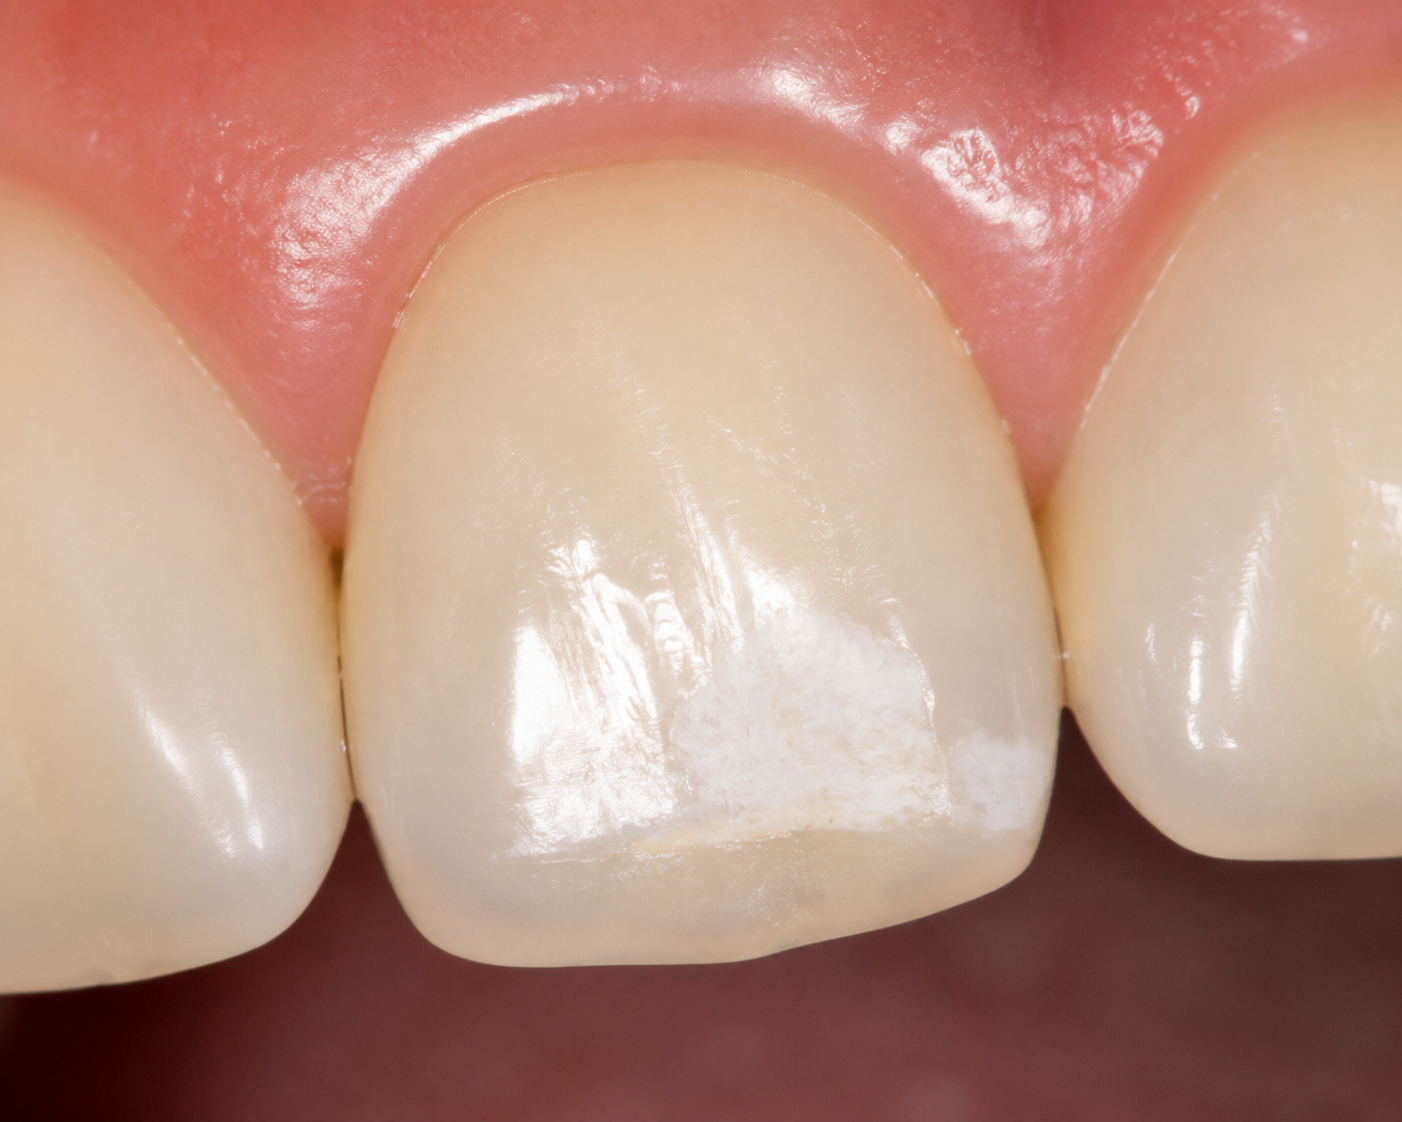
White scars on your teeth aren’t true “scars”—they’re areas where enamel has lost minerals or didn’t form perfectly. Most can be significantly reduced or even erased, especially when the right treatment matches the underlying cause.
That chalky white patch that catches your eye in every mirror has a clinical name: white spot lesion (WSL). It’s an early sign that the enamel—the outermost shield of your tooth—is in distress. While alarming to see, these spots are rarely a dental emergency. They’re incredibly common, particularly after orthodontic treatment, and a growing armamentarium of professional and at-home solutions exists to restore your smile’s uniformity.

What Are White Scars on Teeth, Really?
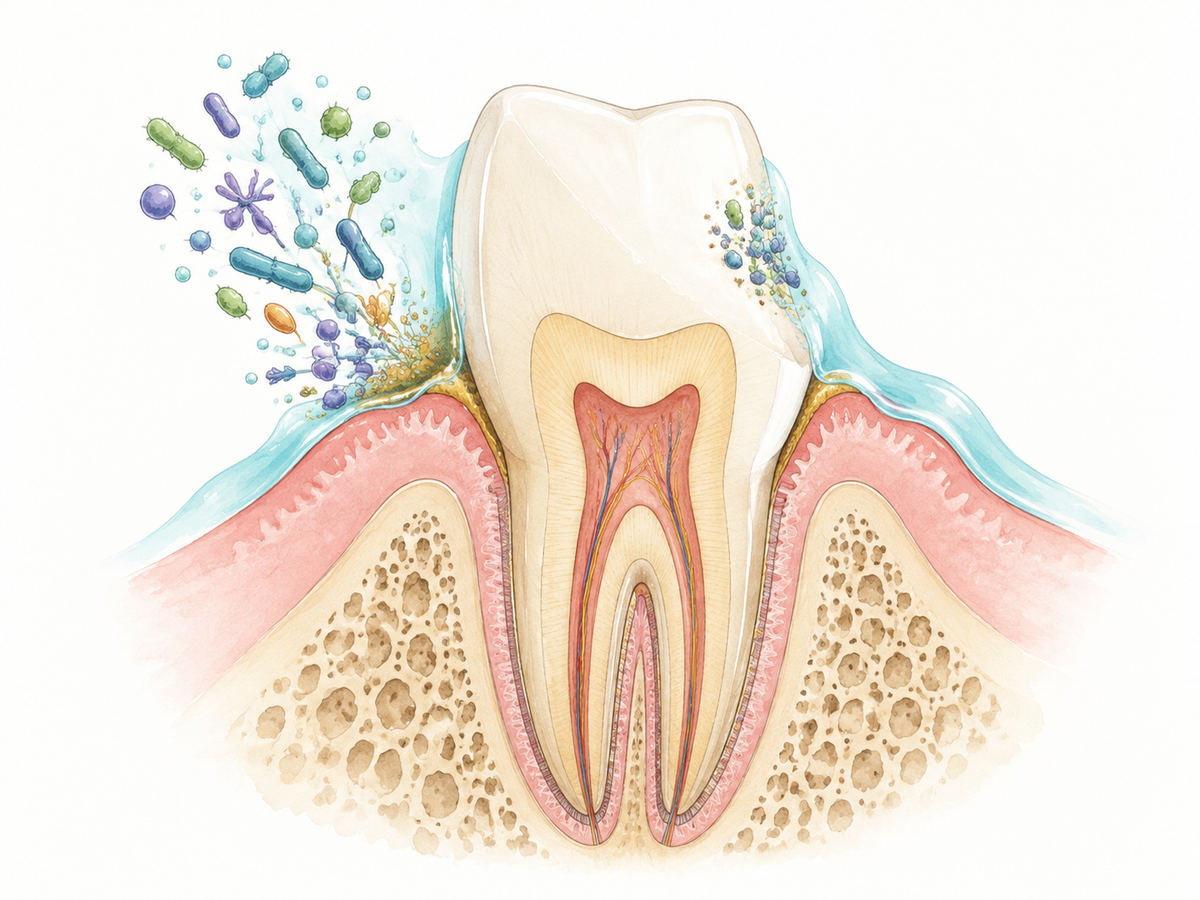
Despite the name, a “white scar” is not a scar in the medical sense. Most often, it’s an area of enamel demineralization (incipient caries)—the very first visible step toward a cavity. When plaque bacteria feast on sugars, they produce acids that pull calcium and phosphate out of the enamel. This creates microscopic pores that scatter light differently, producing a dull white spot. In other cases, the spot formed while the tooth was still developing, either from too much fluoride during childhood (dental fluorosis) or a glitch in enamel formation called enamel hypoplasia. Knowing which camp your spots fall into determines how you’ll get rid of them, because active demineralization can often be remineralized, while intrinsic defects need a masking or restorative approach.
A 2023 systematic review published in BMC Oral Health notes that white spot lesions represent the first stage of caries and their prevalence has been rising, now affecting between 10% and 49% of the population. The good news? Because the surface remains intact, these lesions are relatively easy to arrest and cosmetically improve when caught early.
What Causes Those White Marks?
Understanding the “why” makes the “how to fix it” much clearer. The two major origins—and a less common third—are:

-
Plaque-driven decalcification
Inadequate brushing leaves a sticky film of bacteria on the tooth surface. When you consume fermentable carbohydrates (sugars and starches), the bacteria produce acid that leaches minerals out of the enamel. This happens especially around orthodontic brackets, where cleaning is trickier.
> Almost 97% of people who underwent fixed orthodontic treatment had developed generalized white spot lesions post treatment, according to a review in the Journal of Orthodontic Science. The maxillary lateral incisors and canines are the most frequently affected teeth. -
Dental fluorosis
Ingesting too much fluoride while the permanent teeth were forming (typically before age 8) disrupts the enamel-building cells. This results in intrinsic white streaks or cloudy patches that are present when the tooth erupts. Fluorosis spots are not soft or active; they are stable and typically require mechanical or restorative camouflage. -
Enamel hypoplasia
A developmental defect where the enamel is thinner or missing, appearing as pits, grooves, or white-to-yellowish splotches. These can arise from childhood illness, malnutrition, or genetic factors.
The treatment you choose will hinge on whether the spot is active (still losing minerals, may feel slightly rough) or arrested (hard and unchanged). A dentist uses visual examination, air-drying, and sometimes fluorescence tools to make that call.
Professional Treatments That Deliver Fast, Visible Results
If you want noticeable improvement within a single visit, in-office procedures are the gold standard. They’re especially valuable for spots that have been stable for years or those caused by fluorosis.

Microabrasion
This technique uses a slurry of hydrochloric acid and pumice to gently erode a microscopically thin layer of surface enamel—typically 25–200 µm—removing the superficial white opacity and leaving a smoother, more uniform surface underneath. It’s a fast, conservative option for shallow fluorotic marks or post-orthodontic decalcification. However, deeper lesions may not be fully erased, and the tooth often looks temporarily dull before rehydrating and blending over a few weeks.
Resin Infiltration (Icon Treatment)
Resin infiltration is a minimally invasive breakthrough. After etching the surface with a 15% hydrochloric acid gel to open the pores, a low-viscosity light-curable resin is drawn into the demineralized enamel. Because the resin’s refractive index is extremely close to that of healthy enamel, the white appearance instantly disappears. A 2024 randomized clinical trial showed that teeth treated with resin infiltration had an immediate and significant reduction in color difference compared to fluoride varnish, and the results remained stable at the six-month mark. For mild to moderate fluorosis, repeated etching and a longer infiltration time further boost the outcome, as noted in a systematic review on fluorosis interventions.
Professional Teeth Whitening (Bleaching)
While counterintuitive—won’t whitening just make the spots whiter?—dental bleaching can be a strategic tool. By lightening the surrounding healthy enamel, the contrast between the spot and the tooth decreases, making the entire tooth appear more uniform. This works best with shallow spots and is often combined with microabrasion or resin infiltration in a stepwise fashion. However, in-office whitening requires careful planning: if used alone, some white spots can temporarily become even more opaque due to dehydration, so your dentist might advise a multi-step sequence.
Dental Bonding and Porcelain Veneers
For deeper, larger lesions or those covering the whole facial surface, direct composite bonding or porcelain veneers deliver a complete cosmetic transformation. Bonding sculpts tooth-colored resin directly onto the tooth, while veneers are custom-made ceramic shells that cover the front. Both work well for intrinsic defects like severe fluorosis or hypoplasia. They are more invasive than microabrasion or infiltration, but they provide the ultimate control over color and shape.
A 2023 network meta-analysis in BMC Oral Health that compared seven therapies found that resin infiltration and the combination of a self-assembling peptide (P11-4) with fluoride varnish ranked highest for lesion improvement. Traditional fluoride and CPP-ACP did not show statistically significant cosmetic benefit, supporting the idea that for immediate esthetic gains, you need a physically masking approach.
At-Home Strategies That Support Remineralization
Not every white spot requires a visit to the dentist’s chair. When the lesion is small, active, and positioned where you can keep it plaque-free, at-home remineralization therapy can slowly nudge the enamel back to health.

- Fluoride toothpaste or varnish — Fluoride ions encourage the formation of fluorapatite, a more acid-resistant crystal. For early demineralization, a high-concentration fluoride gel or varnish applied by your dentist can boost this process significantly.
- CPP-ACP (MI Paste) — Derived from milk casein, casein phosphopeptide–amorphous calcium phosphate complexes deliver bioavailable calcium and phosphate to the enamel surface, prompting mineral redeposit. It’s a gentle option, especially for patients avoiding extra fluoride.
- Nano-hydroxyapatite toothpaste — A biomimetic approach that supplies calcium and phosphate in a particle size small enough to fill microscopic tubules and pores. Emerging evidence suggests it can support enamel repair, though large-scale clinical trials are still catching up.
For these products to work, they need a plaque-free surface. Using an electric toothbrush can help remove bacterial biofilm more effectively than a manual brush, giving remineralizing agents the best chance to penetrate the enamel and reverse the white spots.
Be realistic: a month of diligent remineralization may reduce the size and opacity of a shallow white spot, but it won’t make a deep fluorosis mark or a large post-orthodontic lesion disappear completely. If you don’t see gradual fading within 8–12 weeks, it’s time to discuss in-office options.
Mistakes That Can Make White Spots Even More Obvious
Desperation can drive patients toward internet hacks that actively worsen the problem. Recognizing these traps protects your enamel and your investment in treatment.

- Abrasive scrubs — Baking soda, charcoal toothpaste, or “whitening” powders scour the enamel surface. While they might briefly scrub away superficial stains, they also wear down the already-thin enamel over the spot, making the porosity more visible and increasing the risk of further mineral loss.
- DIY acidic whitening rinses — Lemon juice, apple cider vinegar, or even hydrogen peroxide in extremely high concentrations can soften and erode enamel. The white spot may look temporarily less obvious because the surface is now dull and roughened, but the damage is permanent and will soon magnify the discoloration.
- Aggressive bleaching without supervision — Over-the-counter whitening strips or gels used without a dentist’s tray can dehydrate and bleach unevenly. White spots often turn temporarily chalkier and brighter, which can be psychologically devastating if you’re not prepared. If you plan to whiten at home, do it after a remineralization phase and under professional guidance.
Think of it this way: A white spot is already a sign of mineral loss. Anything you do that removes more mineral makes the problem worse.
How to Keep Your Smile Spot-Free for Good
Prevention is the ultimate “removal” strategy. Integrating a few daily habits can stop new white scars from forming and keep existing ones from progressing.

- Limit sugar-sipping and grazing — Each sip of soda, juice, or sweetened coffee feeds acid-producing bacteria. Instead, drink plain water between meals and limit sugary treats to a single sitting, then rinse with water.
- Master the right brushing technique — Brush twice a day for two full minutes, paying special attention to the gumline and any appliance margins. When you brush, use a sonic electric toothbrush to clean thoroughly but gently—aggressive scrubbing can wear away vulnerable enamel and make white spots more visible.
- Fortify with fluoride — A fluoride mouth rinse at a different time than brushing (say, after lunch) can keep a low-level protective effect running all day.
- Manage dry mouth — Saliva is your natural remineralization solution. If you take medications that cause xerostomia, talk to your dentist about saliva substitutes or prescription fluoride gels.
- Keep regular dental check-ups — A professional cleaning every six months removes the biofilm you can’t reach, and your dentist can catch early demineralization before it turns into a cavity.
White spots don’t have to be a permanent sentence. By matching the treatment to the cause—remineralization for active decay, microabrasion or infiltration for stubborn surface marks, and bonding or veneers for deep intrinsic defects—you can reclaim a consistently bright, confident smile. The first step is an accurate diagnosis, so book that exam and start your personal roadmap to spot-free enamel.
This article has been reviewed by an oral health professional for accuracy. It is intended to provide general educational information and should not be used as a substitute for personalized medical advice, diagnosis, or treatment. If you have questions or concerns about your oral health, please consult a dentist, physician, or other qualified healthcare provider.